 The referral pathways guide



 Read with intention













 Meet the clinicians
Echoes of trauma: Recognising the signs of PTSD

If you have lived through something frightening or overwhelming, you may have noticed that the experience does not always stay in the past. A sound, a smell or an unexpected memory can bring it rushing back. Sleep may not come easily. The world can feel less safe than it once did. If any of this sounds familiar, please know that these are recognised, well-understood responses to trauma. They are not a sign of weakness, and effective support is available.
Post-traumatic stress disorder (PTSD) is a treatable mental health condition that can develop after experiencing or witnessing events such as serious accidents, assault, natural disasters, medical emergencies, the sudden loss of a loved one, or combat. According to the World Health Organization, around 70 per cent of people worldwide will experience a potentially traumatic event at some point in their lives, yet only a minority, an estimated 5.6 per cent, go on to develop PTSD.2 In other words, distress after trauma is common and human; PTSD is what can happen when that distress becomes stuck. Understanding what PTSD looks like, and how it differs from an ordinary stress response, is often the first step towards the right help.
What trauma does to the nervous system
When we face danger, the brain’s alarm system triggers the familiar fight, flight or freeze response. This system is centred on a small structure called the amygdala. Stress hormones surge, the heart races, and attention narrows to the threat. This is a healthy survival response, and for most people it settles once the danger has passed.
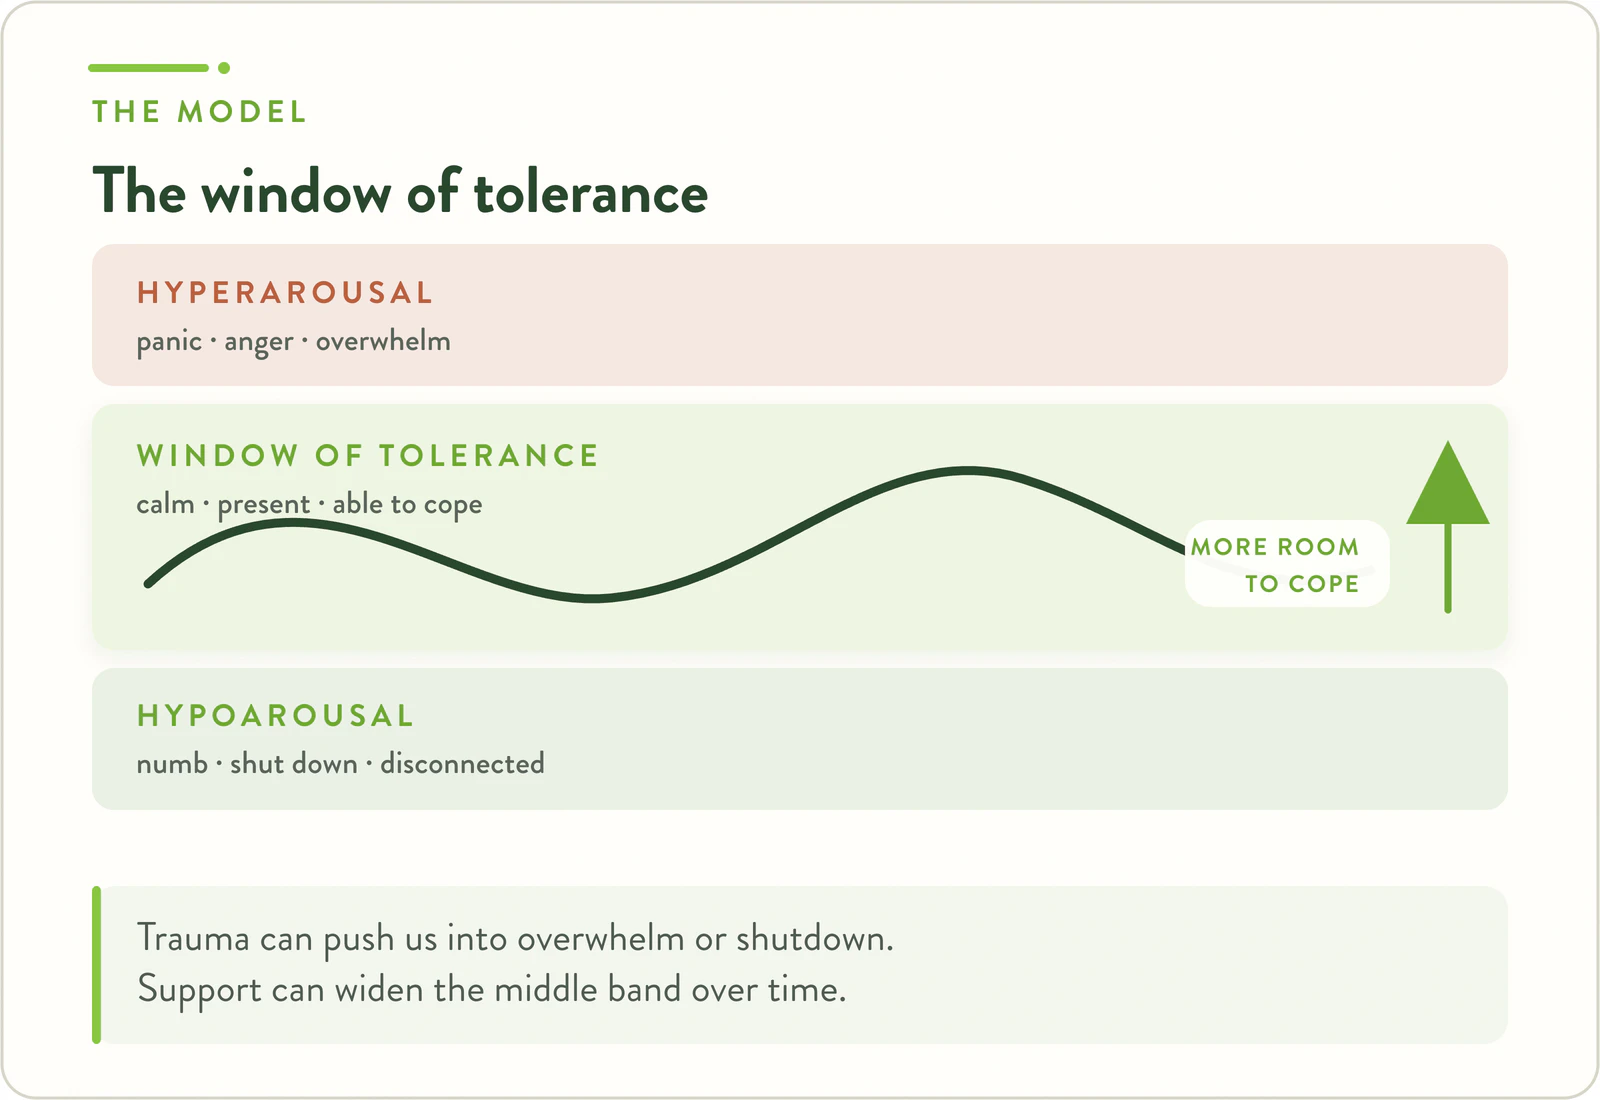
After some traumatic experiences, however, the alarm system does not fully switch off. The brain continues to behave as though the threat is still present, scanning constantly for danger and reacting strongly to reminders. At the same time, the memory of the event may not be stored in the usual way. Rather than settling into the past as a story with a beginning, middle and end, fragments of the memory, such as images, sensations and emotions, can remain vivid and easily triggered, returning with an intensity that feels like now rather than then. This helps explain why people with PTSD are not simply “dwelling on” what happened. Their nervous system is doing its best to protect them, but the protection has become stuck on high alert.
The four symptom clusters of PTSD
The DSM-5-TR, the diagnostic manual used by psychologists and psychiatrists in Australia, groups PTSD symptoms into four clusters.3 You do not need to experience every symptom for your difficulties to matter, but a pattern across these areas lasting more than a month may suggest PTSD.
1. Re-experiencing the trauma
This includes unwanted, intrusive memories of the event; distressing dreams or nightmares; and flashbacks, where it can feel as though the event is happening again. Reminders such as places, anniversaries, sounds and smells may trigger intense emotional distress or physical reactions such as a racing heart, sweating or nausea.
2. Avoidance
Because reminders are so painful, many people begin to avoid them. This might mean steering clear of certain places, people, conversations or activities, or working hard to push away thoughts and feelings connected to the trauma. Avoidance brings short-term relief, but over time it can shrink a person’s world and, unintentionally, keep the trauma response alive.
3. Negative changes in thoughts and mood
Trauma can shift how people see themselves, others and the world. Common experiences include persistent beliefs such as “I am to blame”, “I can’t trust anyone” or “the world is dangerous”; ongoing guilt, shame, fear or anger; feeling emotionally numb or detached from loved ones; losing interest in activities that once brought joy; and difficulty experiencing positive emotions at all.
4. Changes in arousal and reactivity
This cluster reflects the nervous system’s stuck alarm: feeling constantly on guard (hypervigilance), being easily startled, irritability or angry outbursts, difficulty concentrating, trouble falling or staying asleep, and sometimes reckless or self-destructive behaviour. Many people describe feeling exhausted yet unable to relax.
How PTSD differs from a normal stress response
It is important to say clearly: being distressed after a traumatic event is normal. In the days and weeks afterwards, most people experience some combination of intrusive memories, poor sleep, jumpiness and strong emotions. For the majority, these reactions gradually ease as the mind processes what happened, particularly with the support of family, friends and routine.2
PTSD is considered when symptoms persist for more than a month, remain intense or worsen over time, and interfere with daily life, whether that is work, study, relationships or the ability to feel safe.3 The difference is less about what you feel and more about whether the natural recovery process has stalled. Symptoms can also emerge months or even years after the event, sometimes triggered by a reminder or a later stressor, which can be confusing for the person experiencing them.
Complex PTSD, in brief
The World Health Organization’s ICD-11 recognises a related condition called complex PTSD (C-PTSD). It can develop after prolonged or repeated trauma from which escape was difficult or impossible. Examples include childhood abuse or neglect, family violence, or captivity. Alongside the core PTSD symptoms, complex PTSD involves three additional areas of difficulty: managing intense emotions, a deeply negative view of oneself often accompanied by shame or worthlessness, and persistent difficulty feeling close to or trusting others. Recovery is absolutely possible, though therapy may proceed more gradually, with early emphasis on safety, stabilisation and building trust.
Evidence-based treatments for PTSD
PTSD is one of the most researched conditions in mental health. Phoenix Australia, the national centre of excellence in post-traumatic mental health, developed the Australian guidelines, which strongly recommend trauma-focused psychological therapies as first-line treatment.1 The two most established approaches are:2
- Trauma-focused cognitive behavioural therapy (TF-CBT): a structured therapy that helps you gradually and safely process traumatic memories, reduce avoidance, and shift unhelpful beliefs that trauma often leaves behind, such as excessive self-blame. It typically includes psychoeducation, coping skills and carefully paced exposure work, always at a speed you can tolerate.
- Eye movement desensitisation and reprocessing (EMDR): a therapy in which you briefly focus on the traumatic memory while engaging in bilateral stimulation, usually guided eye movements. EMDR appears to help the brain reprocess traumatic memories so they lose their raw, present-tense intensity.
Research shows that many people who complete these therapies experience a meaningful reduction in symptoms, and some no longer meet criteria for PTSD afterwards. Outcomes vary from person to person, and no ethical practitioner can promise a particular result. The evidence base is strong, though, and it is never too late to begin. Medication, usually prescribed by a GP or psychiatrist, can also play a supporting role for some people.
Caring for yourself while you wait for support
If you are waiting for an appointment, there are gentle, practical things that can help steady your nervous system in the meantime:
- Keep a simple routine. Regular sleep and wake times, meals and daylight give your body cues of safety and predictability.
- Practise grounding. When memories intrude, orient to the present: name five things you can see, four you can hear, three you can touch. Slow breathing, with a longer exhale, calms the alarm response.
- Move your body. Walking, swimming or stretching helps discharge stress hormones and supports sleep.
- Go easy on alcohol and other substances. They may numb distress briefly but tend to worsen sleep, mood and anxiety over time.
- Stay connected. You do not have to talk about the trauma; simply spending time with people you trust counters the pull towards isolation.
- Be compassionate with yourself. You are recovering from something real. Healing is rarely linear, and difficult days are not evidence of failure.
When to seek support
Consider reaching out to a psychologist or your GP if, more than a month after a traumatic event, you notice symptoms from the clusters above; if you are avoiding more and more of your life; if sleep, work or relationships are suffering; or if you are using alcohol or other substances to cope. Loved ones sometimes notice changes before we do, so if someone you trust has expressed concern, it may be worth listening.
If you or someone you know is in immediate danger, call 000. For 24/7 crisis support, call Lifeline on 13 11 14. If you are having thoughts of suicide or self-harm, please reach out now, you deserve support today, not just when an appointment becomes available.
If you are unsure where you stand, our free, confidential PCL-5 PTSD screener takes about five minutes and can help you gauge whether your experiences warrant a professional assessment. A screener is not a diagnosis, but it can be a useful starting point for a conversation with your GP or psychologist.
Frequently asked questions
Can PTSD develop months or years after the event?
Yes. While symptoms often begin within the first three months, delayed-onset PTSD is well documented. Some people function well for a long period before symptoms surface, often triggered by a reminder, a life change or a new stressor. Late-emerging symptoms are just as valid, and just as treatable.
What if I’m not sure my experience “counts” as trauma?
Many people minimise what happened to them, especially when others “had it worse”. Trauma is defined partly by the event and partly by how your nervous system experienced it. If something continues to affect your sleep, mood, relationships or sense of safety, it is worth taking seriously, regardless of how it compares with anyone else’s story.
Do I need a referral to see a psychologist?
No referral is needed to see a psychologist privately. However, if your usual GP or MyMedicare practice prepares a Mental Health Treatment Plan, you may be eligible for Medicare rebates for up to 10 individual sessions each calendar year. Your GP can also rule out physical contributors to symptoms such as poor sleep and fatigue.
Is telehealth effective for trauma therapy?
Research indicates that trauma-focused therapies can be delivered effectively via video consultation, and many people appreciate engaging in therapy from a place where they feel safe. If attending in person is difficult, telehealth is a legitimate option rather than a lesser one.
Recovery from trauma is not about forgetting what happened; it is about the memory finally taking its place in the past, so that you can live more fully in the present. Our Ahpra-registered psychologists have been supporting the Parramatta community since 2004, and you can learn more about our trauma treatment services, which are available in person and via telehealth Australia-wide, or request an appointment when you feel ready. Whenever that is, we will meet you there with care.
References
- Phoenix Australia. Australian Guidelines for the Prevention and Treatment of Acute Stress Disorder, Posttraumatic Stress Disorder and Complex PTSD. Melbourne: Phoenix Australia Centre for Posttraumatic Mental Health.
- World Health Organization. Post-traumatic stress disorder (fact sheet). Geneva: WHO.
- American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders (5th ed., text revision; DSM-5-TR). Washington, DC: APA Publishing.
More on trauma & grief.
 Trauma & Grief
Grief and loss: A psychologist’s guide to bereavement and complicated grief
A psychologist’s guide to grief, bereavement and complicated grief, including Prolonged Grief Disorder and when to seek professional…
Mind Health team12 min Trauma & Grief
Moral injury: From hidden wound to clinical recognition, a complete guide
Comprehensive guide to moral injury, from DSM-5-TR recognition to evidence-based treatments. Learn about assessment, symptoms, and recovery pathways…
Mind Health team13 min Trauma & Grief
The window of tolerance: Understanding your nervous system’s optimal zone
Discover the Window of Tolerance, the optimal zone where your nervous system can function at its best. Learn…
Mind Health team5 min
Your next step starts here.
Tell us what's going on and we'll match you with the right psychologist, usually after a free triage. No referral needed to begin.
